Antral follicle count: understanding your fertility ultrasound
Learn how antral follicle count is measured, what it can suggest about ovarian response in IVF and why it is not the same as counting every remaining egg.
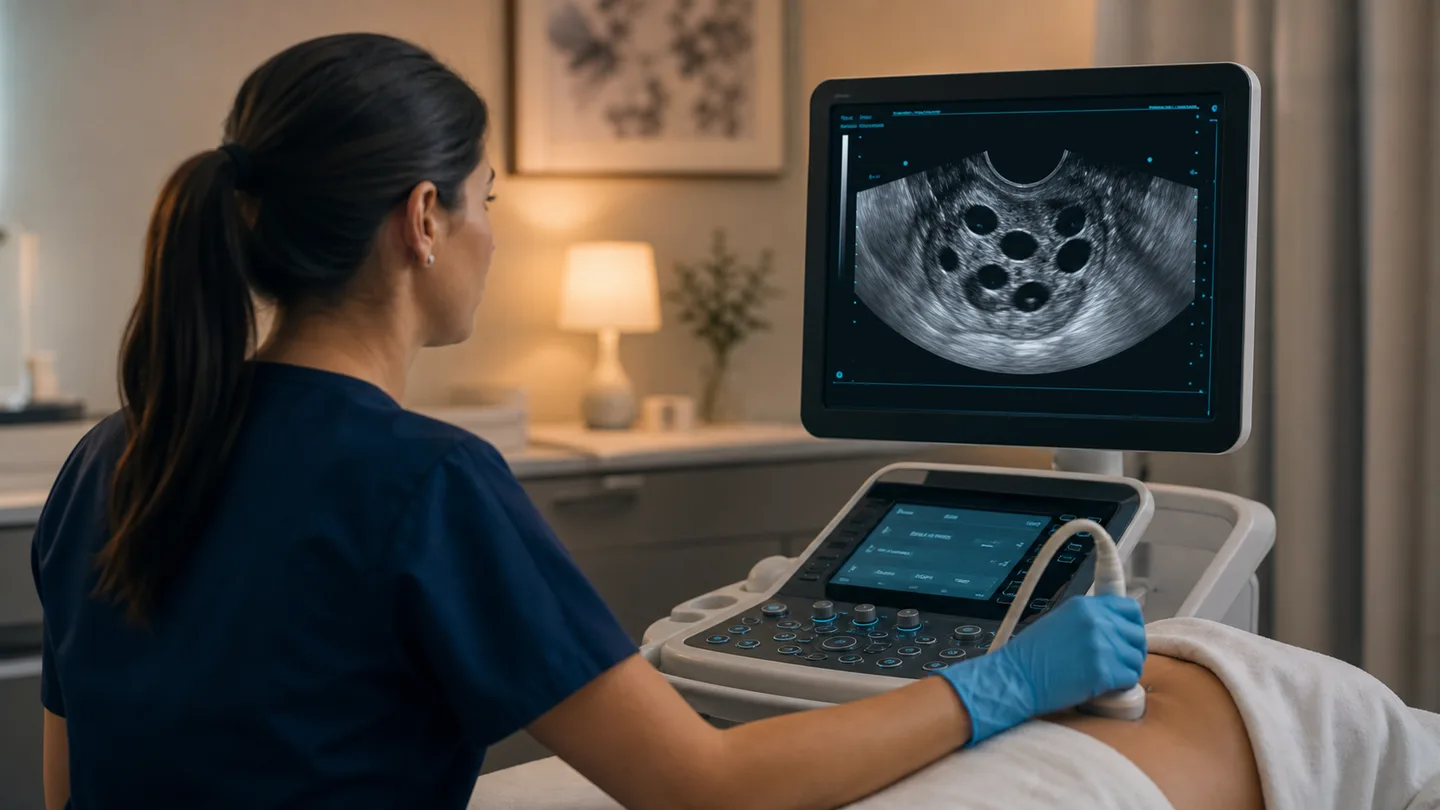
Antral follicle count, usually shortened to AFC, is the total number of small follicles visible in both ovaries during a fertility ultrasound. These fluid-filled structures have begun to grow in the current cycle. A transvaginal scan performed by an experienced professional provides practical information about the likely response to ovarian stimulation.
It is inaccurate to describe AFC as the complete number of eggs left. Ultrasound counts only the antral follicles visible at that moment and cannot directly show the microscopic egg pool. The result is interpreted with age, AMH, previous treatment and the wider clinical history.
How is AFC measured?
The examination is usually performed by transvaginal ultrasound, often during the early follicular phase. The clinician counts antral follicles in both ovaries, commonly those measuring approximately 2–10 millimetres. Equipment, cycle timing and operator experience can all influence the count.
AFC can vary somewhat between cycles, but in experienced centres it is considered a useful measure of ovarian response. If one result differs unexpectedly, the clinician may compare it with earlier scans and hormone results rather than drawing an immediate conclusion.
- Both ovaries are assessed together.
- Size and ovarian appearance are recorded alongside the number.
- The count is never interpreted outside its clinical context.
How does AFC help with an IVF plan?
Antral follicle count helps estimate how many follicles may respond to stimulation. This supports a realistic discussion about starting medicine dose, monitoring needs and likely egg yield. AFC and AMH serve similar purposes and can sometimes provide complementary information.
A low count does not automatically make treatment futile, and a high count does not guarantee pregnancy. A high AFC, particularly with PCOS, can help the team choose a protocol designed to reduce the risk of an excessive response.
Important limits of the count
AFC does not measure egg quality or show an embryo’s chromosome status. Age, sperm findings, embryo development and uterine factors all influence the eventual outcome. Quoting a live-birth probability from AFC alone would therefore be misleading.
For a person without established infertility, AFC is not a test that determines the chance of spontaneous conception. It is a tool for individualizing treatment, not a verdict on someone’s reproductive future.
Frequently asked questions
Which is more accurate, AFC or AMH?
Both are useful for estimating ovarian response and generally provide comparable information. The choice depends on the clinical situation, ultrasound expertise and results already available.
Does a low antral follicle count rule out pregnancy?
No. It may suggest fewer eggs during stimulation, but it cannot give a definite answer about pregnancy. Age and all other fertility factors must also be considered.
To understand how your AFC relates to your own treatment plan, arrange a consultation at Övlad Payı where the ultrasound and full clinical picture can be reviewed together.
Trusted sources
This article is for patient education and does not replace individual medical advice.